
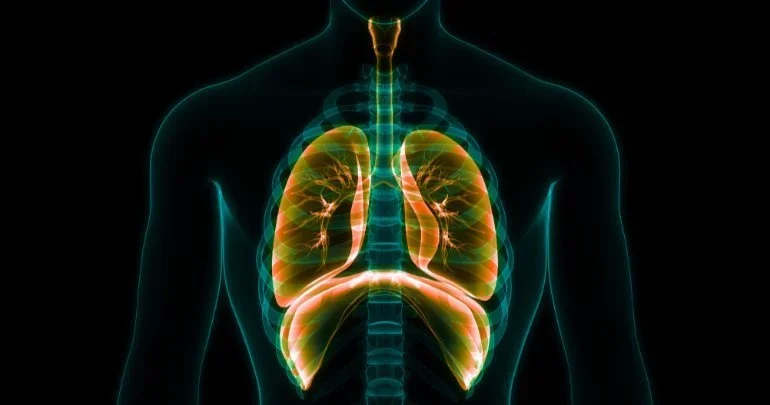
Some orthodontists have recently taken an interest in the function of the airways, nasal passages, nasopharynx, and oropharynx in their practices. To create a more complete picture of optimal breathing, these additional factors also come into play via the craniosacral fascial system:
Larynx
The larynx containing the vocal cords is a key area for voice. Especially notable are the infants diagnosed with laryngomalacia who may still have lingering fascial strain in the larynx.
Trachea
The trachea can follow the same pattern where fascial tightness can cause a chronic cough. Tracheomalacia is a rare condition that needs to be considered in children.
Tracheobroncial Tree
I often see this tightness in children with pediatric asthma. Fascial strain can restrict the tubes that branch off from the trachea, causing impaired breathing.
Lung Air Sacs
On a microscopic level, the tight fascia surrounding the smooth muscles cells of the air sacs can cause the classic wheezing symptoms and pediatric asthma.
Diaphragm
The diaphragm is the main breathing muscle with the many intercostal muscles as secondary responders in the short term. Many patients who cannot belly breathe well need to constantly use these small chest muscles. This is a prime example of the sympathetic nervous system fight-or-flight mode.
I often see many infants with restricted diaphragms. If these tissues do not release on their own during growth, many patients can have impaired breathing because their birth trauma has never been resolved.
The Lower-Body Fascial Web
The lower-body fascial web can pull into the upper body, especially the diaphragm, to create breathing difficulty.
The Upper-Body Fascial Web
The upper body fascial web needs to be free to allow all of the head and neck structures complete freedom to function well.
Optimal breathing requires complete craniosacral fascial freedom of all body structures. Gillespie Approach Training is a great tool for any provider’s toolbox.
